Feeds:
Posts
Comments

Archive for the ‘Uncategorized’ Category


Judas Tree, originally uploaded by bobsee.

This lovely tree is known in France as l’arbre de Judea – which probably relates to its prevalence in the Middle East. However, in English, is has come to be known as the “Judas Tree”. Many authorities believe this is a mistranslation from the French.
However, the story which goes with the name is that Judas hanged himself from this particular variety of tree and it produces its blood red blossom each year after Easter in some kind of remembrance of that.
I find these kinds of stories associated with trees fascinating, and this is one of the first I’ve come across where the story either evolved after the tree’s misnaming, or whether the story influenced the naming.
Does anybody know how this tree really got its name?

by the way, I framed this shot to include the church nearby to heighten the religious connection!

Read Full Post »

I posted about Randy Pausch’s Last Lecture before.

If you haven’t watched it, please go do that now. You won’t regret it.

Yesterday morning Amazon delivered a copy of the book of the lecture. I had decided on the spur of the moment to make the most of the long holiday weekend and fly to Aix so I took the book with me on the plane. Finished reading it this morning. It was a GREAT read. Randy Pausch, for those of you who don’t know this story is a computer scientist who gave a lecture on the “Last Lecture” series at his university. (The idea of the “Last Lecture” is to deliver the lecture you’d deliver if it were to be your last ever). In Randy’s case, he was diagnosed with terminal pancreatic cancer before delivering the lecture, so it really is his last lecture.

The lecture is about how to live life. How to live life abundantly. It’s a true inspiration. And the book covers the same ground but adds some other ideas on the same subject. I’m pretty much in tune with this thinking. I’m a positivist. In fact, one of my colleagues this week put it nicely “You’re ALWAYS bloody positive!” Oh well, hey, I took it as a compliment!

So what lessons did I take from the book that were new to me? The one that hit home was “Ask”. I’m not good at that. Randy tells a great story about going to Disney with his family and his dad saying how great it would be to ride the monorail train up front with the driver. He said to his dad that as he had worked as an Imagineer he knew the secret of how to get to do that and did his dad want to see? Sure, his dad said. So Randy went up to the driver and said “Excuse me, could we ride up front with you?” Sure, said the driver.

Randy’s dad was astonished but Randy said “I said it was a trick. I didn’t say it was a hard trick”.

Ask. You might receive.

Read Full Post »


loch sailing, originally uploaded by bobsee.

There’s something almost universally appealing about sailing boats. Even if you don’t actually like sailing, they are beautiful to see. They have a tall elegance and somehow capture the idea of freedom, pleasure and travel.
I’m not a sailor at all, but I do always find the sight of sailing boats enormously attractive. I wonder what else has this kind of effect? What else is so widely appealing and captures so much symbolically that it adds quality to a day just by being there?

Read Full Post »

Sunday


loch venachar, originally uploaded by bobsee.

How do you spend your days off?
Yesterday (sunday) I had lunch in a little restaurant on the banks of Loch Venachar. It’s lovely to be able to sit outside and eat. There’s something about the relationship between food and health that is so much more than the nutrients that food contains. The social setting and the environment both exert an influence. I think a lot of people forget about that. The way diets are described often breaks food down into its components – as if a component-centred view of life was ever rich or fulfilling!
A common feature of sundays in the UK is the sunday papers – a phenomenon NOT shared by the French! The sunday newspapers in the UK are typically BIG with many sections (most of which I suspect nobody reads!) – but if you were going to sit down and browse your way through the sunday papers, can you think of a better place to read them than outside with a lovely view like this?
(by the way, I don’t know who this couple is…..I just caught them on film)

Read Full Post »

Human beings are complex, dynamic, constantly changing organisms. To understand a single person you have to consider them within their multiple contexts – temporal, spatial, social, cultural and so on. Changes in any of these contexts can profoundly change our understanding of an individual.

Medicine tends to divide all illness into two types – acute and chronic. These terms have the flavour of being defined solely by time – acute is short and chronic lasts longer. But in fact, it’s not that simple. First of all, there is no definite period of time when an acute problem becomes a chronic one. It’s not defined in hours, days or weeks. And there is no transition point, where suddenly a problem is no longer acute, but has become chronic. Secondly, the same disease might at some time be termed acute and at others termed chronic. The taxonomy becomes confusing. There is even talk of “acute on chronic” where a chronic problem , temporarily becomes acute. Sometimes this is termed “relapses and remissions”, but you might think of it as really bad spells within an ongoing illness. In all these definitions, the assumption is what is important, definitive even, is the duration of the problem. The longer the duration, the more likely we will term it chronic. But this tricks our minds into thinking it’s just the same thing, and the only difference is how long the problem lasts.

Here’s a slide I made up to teach medical students and which I share with patient groups too –

acute/chronic

What this slide shows is a graph. If we move from left to right, we consider longer duration of symptoms. If we move from below upwards we consider a greater number of symptoms. There are two circles, one inside the other. The greenish circle represents the set of symptoms which are characteristic of a specific disease – say, for example, asthma. The yellow circle represents the set of symptoms which are experienced by an individual patient and are therefore not characteristic of the disease.

On the left we see the typical “acute” scenario. In the example of asthma, this might be what is termed “status asthmaticus” – a severe, life threatening episode of wheeze. Imagine a series of a hundred children admitted to the emergency department of a hospital with this problem. Almost all of them will have the same symptoms and signs. The variation (as represented by the yellow circle) will be tiny. Such a situation does not require much individualisation of care – they ALL need pretty much the same treatment. Although every one of those hundred children is totally unique, in the “acute” situation, that matters little. They all need the treatment which will open up their airways and allow them to breathe again.

Further along to the right we see the typical “chronic” scenario. Let’s say this represents a series of a hundred children who have had asthma for ten years. They will still all have a set of symptoms characteristic of the disease “asthma” (represented by the greenish circle) but now they will all have a great number of different symptoms and experiences of the disease (represented by the large yellow circle). Some, over the ten years, will have symptoms only when they run, others only in the winter, yet others only in the summer. Some will have found that sitting up in bed eases their cough, others will have found only lying flat on their stomach eases it. Some will have found a glass of cold water will set off a fit of coughing, whilst others will have found that only a glass of cold water settles their coughing. Some will become very irritable when wheezy, others afraid and clingy. In short, the more of the story you listen to you, the more you realise that every single one of these children is unique.

This is the key difference between “acute” and “chronic”. It’s not just a matter of time and we can treat all children with asthma the same way and get the same result. As time passes the individual brings more of themselves into the picture. We all cope differently. We all experience the world differently. We are all impacted differently by the “same disease”.

This is one of the ways the biomedical approach falls down. It’s been fantastic at developing techniques and technologies to deal with acute, life-threatening disease. But the same tools are not enough in chronic illness because chronic is not just long-last acute – it’s fundamentally different.

The management of chronic illness will always be inadequate if it fails to consider the uniqueness of every individual and focuses instead on the small number of symptoms which people with the same disease have in common.

As we move our gaze from the short term to the long term we need to change our focus and our priorities – from the disease to the person.

In essence, the longer term requires a greater emphasis on understanding the individual and tailoring a complex of interventions and supports to bring about the greatest benefits for every single human being considered as unique – not as just another example of disease “x”.

Read Full Post »

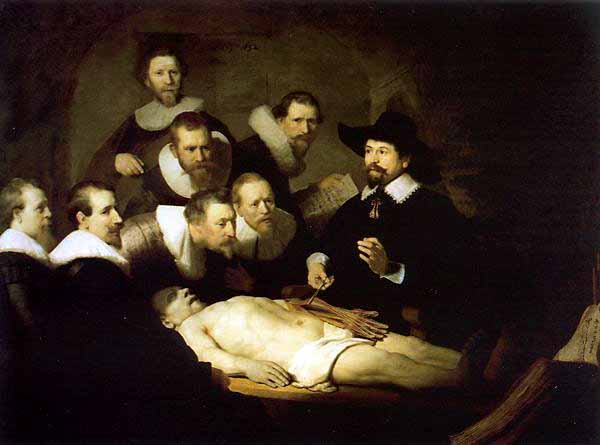
The rationale for what is known as “orthodox”, “Western”, or, more accurately, “biomedical” medicine, is very materialistic. It’s focussed on the physical, and has been since the morbid anatomists of the 15th and 17th century Parisian hospitals began conducting post-mortem dissections and claimed that disease was what you could see, touch, and measure. This reduction of human suffering to physical components was a new phenomenon which was dramatically captured by Rembrandt in The Anatomy Lesson of Dr Tulp.

This combined with Bichat‘s concept of “the lesion” focussed the attention of doctors and scientists on smaller and smaller parts of the human body. The development of the microscope knocked the morbid anatomists off their dominant chairs by showing that disease was not just what you could see and measure with your own eyes, but was actually a disturbance of, and within, cells. Further technological developments allowed smaller and smaller components of human beings to be studied and measured, and this has continued up to the present day, to the extent that “diagnosis” has become the art of interpreting machine-generated measurements of body components and even an examination of DNA.

But human beings are complex adaptive systems, and the more complex a system, the less you can understand it by only examining its parts. Pain cannot be understood by a simple consideration of neural pathways, cell receptors and short chain proteins. Depression cannot be understood by a simple measurement of serotonin levels. And health cannot be understood by adding up a whole list of biological metrics.

As Mary Midgely said,

One cannot claim to know somebody merely because one has collected a pile of printed information about them.

However, most of our interventions are devised within this materialistic and reductionist framework.
Most surgical interventions are intended to remove diseased, or “abnormal” tissue. Most non-surgical interventions involve the use of drugs – manufactured molecules intended to interact with molecules within the human body.

In many cases, this approach pays off. In managing acute, life-threatening disease it is very effective. You are less likely to die in the middle of heart attack, an asthmatic attack or an epileptic fit now than you would have been fifty years ago. The problem lies with chronic illness, where this approach is not nearly so effective. The chances of having heart disease, asthma or epilepsy is greater now than it was fifty years ago, and there are still no cures. There are no known treatments which will cure these chronic problems.

Maybe this is partly because the more chronic the problem, the more unique, the more personal, the experience and its manifestation. Maybe we need a different approach because whole people cannot be understood as mere sums of their parts.

We need to put molecules and materialism into their most useful contexts and not assume that they present the only truth.

We need to design health care around whole people, not bits of them. Let’s have Person Sized Medicine.

Read Full Post »

Yesterday I posted about Seth Godin’s comments about making money.

Today I read an article by Desmond Morris about living to a grand old age. Remember Desmond Morris? He’s the zoologist who wrote “Manwatching“, a book I read as a teenager and found utterly fascinating. Well, he’s 80 years old now and he was writing about ageing. He tells us about Madame Jeanne Calment who lived in Arles until she died aged 122 (at 121 she was the world’s longest living human being). He wondered about her longevity. I’m sure you’ve read articles like that before, where people are interviewed to try and figure out what they were doing that contributed to their experience of health and longevity. Well, the amazing Madame Calment was still cycling and gardening at 121, and had tried to give up cigarettes at the behest of a local doctor a few years before but didn’t manage, and she enjoyed daily cheap, red wine, ate well of a typical French diet including rich stews, fois gras, and chocolates. She joked that her name, Calment, was very appropriate because she was always calm. And this, Morris thinks, was a key characteristic –

Had she worried about her health and taken steps to improve it, the anxiety caused by stirring up fears about ill-health would themselves have reduced the efficiency of her immune system.

Worrying about your health can make you sick! He mentions other long living people who shared this characteristic of not worrying about their health –

The oldest man who ever lived, Mr Izumi of Japan (who made it to 120), enjoyed his daily saki (rice wine) and said his secret was “not worrying”. Eubie Blake, a U.S. jazz pianist, said at his 100th birthday party: “If I’d known I was gonna live this long, I’d have taken better care of myself.” The irony is that it was probably his not worrying about his health that enabled him to live that long.

Regular, gentle exercise, like walking, cycling and gardening are common features of the lives of those who are over 100 years old and Desmond Morris makes an extremely interesting point about the place of exercise in these peoples’ lives. He noted that, when it came to exercise –

Cycling, walking and gardening were three of the most popular – done not to keep fit but for pleasure.

What’s Morris’s conclusion?

It seems that if you wish to live an unusually long life, you need to eat and drink what you fancy, keep as mobile as possible, have a lively interest in the world around you, avoid introspection and, above all, do not waste time worrying about your health.

I like his summary on the place of food in our lives too –

  1. There are three truths concerning human feeding behaviour.
  2. The first recognises that we evolved as omnivores, succeeding where others failed because we consumed a wide range of foods. One of the reasons we are now living longer than we did in the past is that the shelves of supermarkets display a truly astonishing variety of food from all over the world.
  3. The second truth, which renders all diet books superfluous, is that the more you eat, the fatter you get, and the less you eat, the thinner you get. End of story. But whether you are eating more in order to put on weight or eating less in order to lose it, it is always important to keep the range of foodstuffs as wide as possible.
  4. The final food truth is that you should enjoy what you eat and take time to relax while eating it. Speed and anxiety ruin digestion.

Read Full Post »

The UK government has announced this week that it is to roll out a screening programme – “Health MOTs” – checking blood pressure, height, weight, age, current medication, family history and whether a patient smokes and include a simple blood test to check cholesterol and, in some cases, sugar.

Patients with abnormal results will be offered advice, blood pressure drugs and/or statins.

Announcing the plans, Alan Johnson, the Health Secretary, said screening could save 2,000 lives a year

This is an old but much peddled nonsense.

The mortality rate for human beings is 100%. Everybody dies. Reducing the numbers of people dying from one particular disease inevitably increases the numbers dying from something else – people don’t die healthy! But there is virtually no debate at all about this. I’ve never read a single piece of research which asks the question – if less people die from heart disease and strokes, what will they die from instead? Does anybody know? Does anybody care? Well, they should do.

Let me be clear. If there are effective interventions and treatments for any diseases, we should use them. I’m not saying it would be good NOT to reduce heart disease. However, I’d like to know two things – firstly, those who have been treated after a heart disease risk factor is picked up in screening…….what life experience do they have? What diseases are increased in this group? (do we see more cancer, more dementia, more degenerative diseases for example?) And, secondly, more specifically what is the life experience of this group who are put onto drugs for decades after screening? (lifestyle interventions are likely to have positive impacts on a wide range of diseases, but drugs for preventing specific diseases only, at best, impact on those particular diseases)

I think that we need to start thinking of health, not in the short term, but from what has been termed a “life course” perspective. Without that, we are barreling in, at best, semi-blind.

Read Full Post »

Here’s an astonishing calculation. In England, in 2006, there were 16 million admissions to hospitals. That’s an astonishing number for a population of about 50 million!

As if that’s not astonishing enough, 6.5% of those admissions were for patients who were suffering from the bad effects of prescribed medicines. That works out at 1,040,000 patients!

At an average of £228 per day as the cost of a hospital stay and and an average of 8 days admission for each of these patients, the cost to the NHS in England in 2006 was £1,896,960,000.

Compass, the organisation which made this calculation concludes –

“Now is the time for a debate about costs and policies about which drugs the healthcare service can afford as people are paying infinitely higher prices – the drugs bill to the NHS now stands at £11bn – for increasingly marginal rewards and higher risk from adverse drug reactions.”

These figures are part of a trend. Every year the drugs bill gets higher and every year the cost of treating people for the adverse effects of prescribed drugs goes up. This isn’t a sustainable path. Is anybody thinking we need a re-think about health care?

Read Full Post »

Favourite trees

I think trees have a special place in human imagination. Forests have mythical status, offering protection, or harbouring threat. It’s probably partly because trees can live for so many more years than humans can. During the “great flu” early in the twentieth century which killed millions of people, sangomas in Africa, and shamans in Alaska claimed that the villages which were built around great trees had far fewer deaths from flu than those which weren’t. I don’t think that’s ever been shown to be true, but it shows how the myths of the protective power of trees is universal. A great tree can have protective powers, can be a source of healing. I could tell you a couple of really interesting stories about healing trees, but I’ll leave them to another post.

My grandfather would talk about “The Big Tree” and I have a very clear image in my head of a black and white photo of him standing under “The Big Tree”. It’s a tree growing in one of the main streets of Kirkwall, in Orkney. I also remember seeing that tree enclosed in iron railings. I always thought that was a bit sad, as if the tree was imprisoned, although I suspect the railings were there to protect the tree.

The Man Who Planted Trees, by Jean Giono, is one of my most favourite books. It’s a true hero story, a narrative of the power of one person’s actions in transforming the world. American readers are probably familiar with Johnny Appleseed, which has similar narrative characteristics. I can also recommend The Story of Yew, by Guido Mina di Sospiro, whose narrator is a tree. It’s botanically informative, opening your eyes to the amazing wonder of trees, and it’s a thought-provoking tale which makes you think about life. The third book on my bookshelf about trees is Eucalyptus, by the Australian author, Murray Bail, a kind of classic fairy tale of the man who wants the hand of the princess and has to complete the challenge set by her father to do so. The challenge is to name every one of the hundreds of Eucalyptus trees he has planted on his ground.

So, in the light of that, have a look at this photo –

Castle tree

I expect you can see lots of trees around Stirling Castle here, but there’s one, right up there by the castle which catches your eye, isn’t there?

Tree closer

That tree is one of my all time favourites. I see it probably every day. Have you got any favourite trees? Like to tell me about them?

Read Full Post »

« Newer Posts - Older Posts »