Feeds:
Posts
Comments

Human beings are complex, dynamic, constantly changing organisms. To understand a single person you have to consider them within their multiple contexts – temporal, spatial, social, cultural and so on. Changes in any of these contexts can profoundly change our understanding of an individual.

Medicine tends to divide all illness into two types – acute and chronic. These terms have the flavour of being defined solely by time – acute is short and chronic lasts longer. But in fact, it’s not that simple. First of all, there is no definite period of time when an acute problem becomes a chronic one. It’s not defined in hours, days or weeks. And there is no transition point, where suddenly a problem is no longer acute, but has become chronic. Secondly, the same disease might at some time be termed acute and at others termed chronic. The taxonomy becomes confusing. There is even talk of “acute on chronic” where a chronic problem , temporarily becomes acute. Sometimes this is termed “relapses and remissions”, but you might think of it as really bad spells within an ongoing illness. In all these definitions, the assumption is what is important, definitive even, is the duration of the problem. The longer the duration, the more likely we will term it chronic. But this tricks our minds into thinking it’s just the same thing, and the only difference is how long the problem lasts.

Here’s a slide I made up to teach medical students and which I share with patient groups too –

acute/chronic

What this slide shows is a graph. If we move from left to right, we consider longer duration of symptoms. If we move from below upwards we consider a greater number of symptoms. There are two circles, one inside the other. The greenish circle represents the set of symptoms which are characteristic of a specific disease – say, for example, asthma. The yellow circle represents the set of symptoms which are experienced by an individual patient and are therefore not characteristic of the disease.

On the left we see the typical “acute” scenario. In the example of asthma, this might be what is termed “status asthmaticus” – a severe, life threatening episode of wheeze. Imagine a series of a hundred children admitted to the emergency department of a hospital with this problem. Almost all of them will have the same symptoms and signs. The variation (as represented by the yellow circle) will be tiny. Such a situation does not require much individualisation of care – they ALL need pretty much the same treatment. Although every one of those hundred children is totally unique, in the “acute” situation, that matters little. They all need the treatment which will open up their airways and allow them to breathe again.

Further along to the right we see the typical “chronic” scenario. Let’s say this represents a series of a hundred children who have had asthma for ten years. They will still all have a set of symptoms characteristic of the disease “asthma” (represented by the greenish circle) but now they will all have a great number of different symptoms and experiences of the disease (represented by the large yellow circle). Some, over the ten years, will have symptoms only when they run, others only in the winter, yet others only in the summer. Some will have found that sitting up in bed eases their cough, others will have found only lying flat on their stomach eases it. Some will have found a glass of cold water will set off a fit of coughing, whilst others will have found that only a glass of cold water settles their coughing. Some will become very irritable when wheezy, others afraid and clingy. In short, the more of the story you listen to you, the more you realise that every single one of these children is unique.

This is the key difference between “acute” and “chronic”. It’s not just a matter of time and we can treat all children with asthma the same way and get the same result. As time passes the individual brings more of themselves into the picture. We all cope differently. We all experience the world differently. We are all impacted differently by the “same disease”.

This is one of the ways the biomedical approach falls down. It’s been fantastic at developing techniques and technologies to deal with acute, life-threatening disease. But the same tools are not enough in chronic illness because chronic is not just long-last acute – it’s fundamentally different.

The management of chronic illness will always be inadequate if it fails to consider the uniqueness of every individual and focuses instead on the small number of symptoms which people with the same disease have in common.

As we move our gaze from the short term to the long term we need to change our focus and our priorities – from the disease to the person.

In essence, the longer term requires a greater emphasis on understanding the individual and tailoring a complex of interventions and supports to bring about the greatest benefits for every single human being considered as unique – not as just another example of disease “x”.
Happy-go-lucky

I’m a big fan of Mike Leigh, but although there is a lot of humour in many of his movies, they’re generally pretty dark. His latest movie, Happy-go-lucky, is quite different, yet it retains those essential characteristics of Mike Leigh films – I can’t quite explain it but he manages to make you both care about and squirm about his characters. But what they do more than anything else is highlight what it means to be human, with all the frailty and awkwardness that comes as part of the package.

Happy-go-lucky tells the story of Poppy, a Primary School teacher in London. She’s a single 30 year old with a totally irrepressible positive spirit. She’s smiles a lot, laughs a lot, jokes a lot. Even when she encounters difficulties she deals with them positively. At one point in the movie, she’s told “You can’t make everybody happy” and she replies that it’s worth trying.

My favourite scenes are the flamenco classes. Flamenco always moves me. I love its passion and its fire. The Spanish flamenco dance teacher whose class Poppy attends is brilliant – probably one of the best characters in the whole movie. You can see a couple of scenes in this Channel 4 interview with Mike Leigh –

I have a very positive spirit. In fact, I don’t really see the point in taking a negative attitude to life. I’m pretty sure the stance we take determines the experiences we get.

There’s an area of the brain known as the striatum. This particular area is affected by certain diseases (Parkinsons Disease for example). One of the odd things that happens sometimes when patients are treated with drugs for Parkinsons Disease, is that they can develop strange behaviours in relation to money – compulsive gambling for example.

Some recent studies using fMRI scans, have shown how this area of the brain (the striatum) becomes active when people received either monetary or social rewards

By directly contrasting the brain activities of the same subjects in relation to the delivery of social and monetary rewards, our results clearly show that social approval shares the same neural basis as monetary rewards, thus providing strong support for the idea of a ‘common neural currency’ of reward,” concluded the researchers.

Our findings indicate that the social reward of a good reputation in the eyes of others is processed in an anatomically and functionally similar manner to monetary rewards

The researchers point out that social status affects well-being, morbidity and even survival. They cite an old study conducted on civil servants in England which showed that the lower the employee in the hierarchy, the more likely he or she would develop heart disease.

How others see us, and how that results in our status within society is linked to our neuronal responses to rewards and punishments so intimately, and our nervous system is so linked to our immune system, and our endocrine (hormone) system, that it can actually be a life or death issue.

This shows why it’s important to understand a person, and a person within his or her social networks if we really want to promote health and deal with disease. Simply lowering blood pressure, or cholesterol levels with drugs, is just not enough.

I’m very taken by network theory. Linked is one of the most inspiring books I’ve ever read, and books like The Medici Effect, and Smart World develop aspects of network theory too. Currently I’m reading Clay Shirky’s Here Comes Everybody and he makes this simple but thought-provoking point –

Individuals in group settings exhibit behaviours that no one could predict by studying single minds. No one has ever been bashful or extroverted while sitting alone in their room, no one can be a social climber or a man of the people without reference to society, and these characteristics exist because groups are not just simple aggregations of individuals.

What characteristics do you think you have which only appear when you are in a group?

TED has a great short video of a scientist called Christopher deCharms explaining some of the possibilities of functional brain scans – “fMRI”s.

This is a fascinating technology – looks like a brain scan but in colour. The active areas of the brain “light up” in bright colours which allows us to map functions, including thoughts and feelings. This is letting us develop new levels of understanding about how the brain works.

I’ve seen this sort of technology explained before but what especially excited me about this short talk is the demonstration of its use as a type of biofeedback. You will see an example of a patient with chronic pain interacting with the scan to actually increase the release of the brain’s natural painkillers (endorphins) and reduce his pain.

The potential, only hinted at here, is of technologies which will allow us to access natural ways of dealing with our own illnesses.

I’m reading Clay Shirky’s “Here Comes Everybody” (and, oh, how I’m enjoying it!). Quite early in the book he says this –

….in the words of the physicist Philip Anderson, that “more is different”. Writing in Science magazine in 1972, Anderson noted that aggregations of anything from atoms to people exhibit complex behaviour that cannot be predicted by observing the component parts. Chemistry isn’t just applied physics – you cannot understand all the properties of water from studying its constituent atoms in isolation.

How true! And imagine how that applies even more so to the complexity of biological organisms. You really cannot understand a human being by only studying his or her component parts. One day, health care will catch up with that simple insight!

The biomedical approach to health and illness, not only puts lesions, or pathological changes in the body’s tissues or symptoms, at the heart of diagnosis and treatment. The idea is that disease is a physical phenomenon, with changes which can observed and/or measured. However, what drives patients to consult doctors is frequently not the sudden appearance of a lesion which can be seen. Rather, it’s often the experience of a symptom. Some of the commonest symptoms include pain, weakness and dizziness.

Researchers who have studied patients with common symptoms have found that in a large proportion of cases, there are no objective findings which might explain the presence of the symptoms. This may be dismissed as “in yer heid”, or “nothing wrong” but both of these judgements are unfair and inaccurate. The occurrence of symptoms in the absence of detectable tissue changes has been labelled “Medically Unexplained Symptoms” (MUS) This is a very, very common situation. Different studies have shown that a lack of a medical explanation may occur in 30% of all consultations at a Primary Care level, and in up to 85% of those with particular, common symptoms.

This is really a big problem.

  1. Firstly, all treatments, surgical or pharmacological, are directed against lesions – measurable, pathological changes in tissues or systems. So, in the absence of such pathology, modern medicine’s tools are hopelessly inadequate.
  2. Secondly, non-surgical and non-pharmacological treatments are not well developed, tested or proven, so patients in this situation often end up with operations or drugs because no other solutions are known, and these interventions all carry risks of harm, so patients find that not only are they not helped, but they end up worse off because of side-effects and other iatrogenic harms.
  3. Thirdly, patients in such a predicament often find their suffering dismissed as either psychological and sent for psychiatric treatment, or, worse, find that they nobody actually believes that they are experiencing the suffering they are complaining of.
  4. Fourthly, (and this one is hardly ever mentioned), the existence of “MUS” suggests that symptoms are not the reliable indicators of disease which doctors assume them to be. This leads to the problem of patients whose symptoms are ascribed wrongly to the discovery of pathology. Just because some inflammation is found, or a growth is found, it does not mean that this pathology is the whole cause of the symptoms which the patient is experiencing. In fact, it does not even mean that the pathology is the partial cause of the symptoms. This can lead to the prescription of drugs or the carrying out of surgical procedures which make absolutely no impact on the patient’s suffering.

The concept of “Complex Adaptive Systems” gives us another whole way of understanding such diverse and difficult symptoms – the problem need not lie in a body tissue or in the mind – the problem can lie in maladaptation or malfunctioning of the system as a whole. Such a concept leads to a demand for holistic interventions, because no simple, single-explanation, solutions can work.

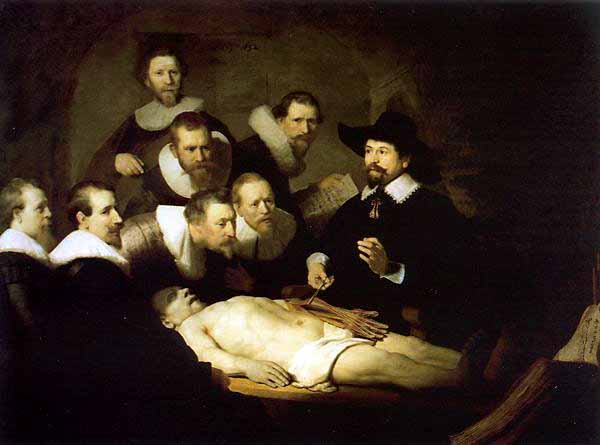
The rationale for what is known as “orthodox”, “Western”, or, more accurately, “biomedical” medicine, is very materialistic. It’s focussed on the physical, and has been since the morbid anatomists of the 15th and 17th century Parisian hospitals began conducting post-mortem dissections and claimed that disease was what you could see, touch, and measure. This reduction of human suffering to physical components was a new phenomenon which was dramatically captured by Rembrandt in The Anatomy Lesson of Dr Tulp.

This combined with Bichat‘s concept of “the lesion” focussed the attention of doctors and scientists on smaller and smaller parts of the human body. The development of the microscope knocked the morbid anatomists off their dominant chairs by showing that disease was not just what you could see and measure with your own eyes, but was actually a disturbance of, and within, cells. Further technological developments allowed smaller and smaller components of human beings to be studied and measured, and this has continued up to the present day, to the extent that “diagnosis” has become the art of interpreting machine-generated measurements of body components and even an examination of DNA.

But human beings are complex adaptive systems, and the more complex a system, the less you can understand it by only examining its parts. Pain cannot be understood by a simple consideration of neural pathways, cell receptors and short chain proteins. Depression cannot be understood by a simple measurement of serotonin levels. And health cannot be understood by adding up a whole list of biological metrics.

As Mary Midgely said,

One cannot claim to know somebody merely because one has collected a pile of printed information about them.

However, most of our interventions are devised within this materialistic and reductionist framework.
Most surgical interventions are intended to remove diseased, or “abnormal” tissue. Most non-surgical interventions involve the use of drugs – manufactured molecules intended to interact with molecules within the human body.

In many cases, this approach pays off. In managing acute, life-threatening disease it is very effective. You are less likely to die in the middle of heart attack, an asthmatic attack or an epileptic fit now than you would have been fifty years ago. The problem lies with chronic illness, where this approach is not nearly so effective. The chances of having heart disease, asthma or epilepsy is greater now than it was fifty years ago, and there are still no cures. There are no known treatments which will cure these chronic problems.

Maybe this is partly because the more chronic the problem, the more unique, the more personal, the experience and its manifestation. Maybe we need a different approach because whole people cannot be understood as mere sums of their parts.

We need to put molecules and materialism into their most useful contexts and not assume that they present the only truth.

We need to design health care around whole people, not bits of them. Let’s have Person Sized Medicine.

Yesterday I posted about Seth Godin’s comments about making money.

Today I read an article by Desmond Morris about living to a grand old age. Remember Desmond Morris? He’s the zoologist who wrote “Manwatching“, a book I read as a teenager and found utterly fascinating. Well, he’s 80 years old now and he was writing about ageing. He tells us about Madame Jeanne Calment who lived in Arles until she died aged 122 (at 121 she was the world’s longest living human being). He wondered about her longevity. I’m sure you’ve read articles like that before, where people are interviewed to try and figure out what they were doing that contributed to their experience of health and longevity. Well, the amazing Madame Calment was still cycling and gardening at 121, and had tried to give up cigarettes at the behest of a local doctor a few years before but didn’t manage, and she enjoyed daily cheap, red wine, ate well of a typical French diet including rich stews, fois gras, and chocolates. She joked that her name, Calment, was very appropriate because she was always calm. And this, Morris thinks, was a key characteristic –

Had she worried about her health and taken steps to improve it, the anxiety caused by stirring up fears about ill-health would themselves have reduced the efficiency of her immune system.

Worrying about your health can make you sick! He mentions other long living people who shared this characteristic of not worrying about their health –

The oldest man who ever lived, Mr Izumi of Japan (who made it to 120), enjoyed his daily saki (rice wine) and said his secret was “not worrying”. Eubie Blake, a U.S. jazz pianist, said at his 100th birthday party: “If I’d known I was gonna live this long, I’d have taken better care of myself.” The irony is that it was probably his not worrying about his health that enabled him to live that long.

Regular, gentle exercise, like walking, cycling and gardening are common features of the lives of those who are over 100 years old and Desmond Morris makes an extremely interesting point about the place of exercise in these peoples’ lives. He noted that, when it came to exercise –

Cycling, walking and gardening were three of the most popular – done not to keep fit but for pleasure.

What’s Morris’s conclusion?

It seems that if you wish to live an unusually long life, you need to eat and drink what you fancy, keep as mobile as possible, have a lively interest in the world around you, avoid introspection and, above all, do not waste time worrying about your health.

I like his summary on the place of food in our lives too –

  1. There are three truths concerning human feeding behaviour.
  2. The first recognises that we evolved as omnivores, succeeding where others failed because we consumed a wide range of foods. One of the reasons we are now living longer than we did in the past is that the shelves of supermarkets display a truly astonishing variety of food from all over the world.
  3. The second truth, which renders all diet books superfluous, is that the more you eat, the fatter you get, and the less you eat, the thinner you get. End of story. But whether you are eating more in order to put on weight or eating less in order to lose it, it is always important to keep the range of foodstuffs as wide as possible.
  4. The final food truth is that you should enjoy what you eat and take time to relax while eating it. Speed and anxiety ruin digestion.

Seth Godin is one of my favourite bloggers. I have his blog on my rss feed reader (google reader) and I frequently enjoy his short, thought-provoking posts.

Today he posted a piece entitled The wealthy gardener where he mentions that he was asked at a talk how to make a lot of money blogging. Seth says he wouldn’t be surprised if at another talk on orchid growing somebody asks how to make a lot of money growing orchids.

He says

Sure, people make money growing orchids. Some people probably get rich growing orchids. Not many though. And my guess is that the people who do make money gardening probably didn’t set out to do so.

The lesson he says is

the benefits kick in best when you don’t set out to achieve them.

This is a very different counsel from the one we read more commonly – that the way to get what you want is to set it as a clear goal, visualise it, then pursue it relentlessly.

I like this message – I think you should do what you feel passionate about – and sometimes, sure, that activity might bring a decent income.

What do you think?